Get Premium
Dark mode theme is available exclusively for premium users. Learn more about the benefits of subscribing.
No fees, cancel anytime.

 Dark Mode Ad-Free Browsing Unlimited Content

 Ad-Free Browsing Unlimited Content Dark Mode
Join 1.2 million Panda readers who get the best art, memes, and fun stories every week!

Going to the doctor can be a scary prospect for many because it could end up revealing health issues that most folks don’t want to confront. Beyond that obvious worry about getting checked out, they might be even more concerned after learning what's happening beneath the surface in hospitals.
That’s why these brave people came forward to expose what medical practitioners have normalized, even though it's all absolutely horrifying. Some of this can be shocking to read, but hopefully it'll help you stay in the know.
This post may include affiliate links.
 Gynecological procedures like punch biopsies and ablations being done without any form of anesthesia or pain control, and women being told they don’t need it…these are extremely painful procedures on very delicate areas. It’s barbaric.
 The long hours Junior doctors work while being expected to have sharp faculties despite being sleep deprived.

Overworking, underpaying and understaffing medical workers. It is amazing to me how much so many things we put money towards that affects our lives and health are being taken away from us so the government fat cats can keep stuffing their pockets. Nixon was kicked out of office because he was a hate monger and resigned because he got caught doing wrong. The people who were presidents that made so many changes for the good of the people have been replaced by malignant narcissists who only benefit themselves at your expense. If you think the U.S. is going to hell, you might want to consider if you voted MAGA, you brought this on for all of us.
 Insurance companies being the decision maker in patients health care.
In the past, doctors and medical professionals were still in the dark about a lot of things that we consider very obvious today, which is why they sometimes used solutions that were barbaric. According to Tim Newman, since the rate of infant mortality was sky-high back in the day, physicians somehow believed that baby teeth were responsible for this situation.
That’s why doctors began combating teething by placing leeches in the kids’ mouths, burning the back of their heads, or even lancing their gums. The latter process became so popular that physicians would sometimes repeat the procedure up to 10 times, which, ironically, could have also led to infection, thereby ruining the little one’s chances of survival.
 The major metropolitan level 1 trauma center I worked at was VERY routinely alarmingly understaffed and people suffered all the time as a result. Especially at night. And a majority of the nurses were in their 20s with less than 5 years of experience, taking on upwards of 6-7 critical patients at a time. Most everyone tried their hardest but with a lack of experience and being completely overburdened, the system put us in impossible scenarios that lead to mistakes, accidents, and all sorts of critical events. I quit and found a safer ER because I couldn't take the stress of feeling like I could hurt someone at work every shift (not intentionally obviously).
Well, you will be overjoyed to find about US health professionals changing careers due to overwork or simply leaving trumpistan all together. Saw an interview of one who left the country. Said in the us almost half her time was spent dealing with health insurance companies, now she just practices medicine.
 How women are treated. Particularly gynecological procedures with no pain management.
Also, took 10 years to develop ED medications to treat a normal part of aging in men, but it takes an average of 10 years to diagnose endometriosis in women, a thing 1 in 10 women suffer, and can cause infertility and organ damage. But the good news is that it's being found in men now too, so I guess they'll actually study it now.
 I don’t do them anymore, but at one point in my career I did esophagectomies (removing part of the esophagus) for cancers. We make an incision in the abdomen, and in the side of the neck, then we have to free up the esophagus itself so it can be removed.
I have very small hands, so my major role was doing the freeing-up part. This was important because we didn’t want to put too much pressure on the heart and decrease the blood flow, and surgeons with big hands have to go much slower at this stage.
I would insert my hand into the abdomen, then up through the diaphragm into the chest cavity, gently wiggling my fingers as I went all the way up the esophagus.
Victory was achieved when I was elbow- or shoulder deep in the patient’s body, wiggling my fingers out the neck hole.
Tiny hands means I’m also really good at getting foreign objects out of butts. My job is so glamorous. 😑.
Some of the things that doctors, nurses, and medical staff have normalized can seem cruel or unusual to laypeople. It might even increase people’s anxiety about a simple checkup, which is why Michelle Crouch shares a few useful healthcare tips that folks can follow if they have to go to the doctor.
One thing to keep in mind: you might be better off visiting a teaching hospital if you need a surgical procedure, as they often have the latest equipment, residents and staff ask more questions, and they pay closer attention to patients. Teaching hospitals also tend to have lower complication rates.
 Feeding tubes on elderly dementia/alzheimers people. Horrible procedure to put someone through that is already confused and anxious at baseline now they have a foreign body to pull on and hurt themselves. Let these people go. We did them with SEDATION and they had to be TIED TO THE TABLE.
 CPR on 90 year olds.

Movies have a lot to answer for. CPR is brutal. To be effective you have to break the ribs.
 From someone that works in nursing, PLEASE have that conversation about a DNAR well in advance of it actually being needed. I cannot count the amount of families that don't want to talk about it and tell us we'll discuss it 'when the time comes.'
Madam, that time is absolutely not when I'm having to do ultimately fruitless CPR on your 98 year old grandpa with severe pneumonia because you and your family are in denial.
One of my standout memories early in my career is dealing with a situation like that, breaking ribs and then documenting the d***h before having to walk of the room like nothing happened, do a meds round, then put on a fun, smiley work face for a resident's Christmas party an hour later.
Shout out to the amazing colleagues and black sense of humour that keep me here 15 years down the line!
If you’re a patient hoping to get the best treatment and leave in one piece, research suggests the best way to do that is to avoid being a distraction. This is because when patients draw a doctor's or nurse’s attention away from what they are doing, errors increase by 12%.
Of course, almost everyone working in a hospital is used to multitasking or getting their focus pulled away every couple of minutes. Still, if a nurse is interrupted 4 times while administering medicine, they are more likely to give a harmful dose, which can have major consequences for the patient.
 The amount of cursing and inappropriate jokes during cardiac surgery would blow your mind, and make anyone from HR freak out. They are very insular rooms, so everyone knows each other well. They have to let off steam because they are in extremely stressful situations often.
I don't mind, as long as they're good at their jobs. I could curse and tell terrible jokes with them too if I were awake. With their help, maybe one day I could.
Abandoning people to suffer excruciating daily pain because the o****d crisis has swung too far in the other direction.
 I think something that was jarring for me when I first became a doctor was just how casually we’ll talk about someone’s impending d***h, even before we tell the family because we don’t think they’re prepared to hear about it just yet.
“Mr. Smith? Oh yeah that guy is definitely not making it out of here, DC to JC (discharge to Jesus Christ).”
Obviously when the time comes to have this conversation with family, it’s about being forward but supportive and helping guide them through what is probably the absolute worst day of their life. Those meetings are hard. But outside those meetings everyone is just like *shrug* *.

I believe that's one of the few ways to cope. I'm a train driver so I also meet d***h on the job, thankfully not nearly as frequently, but we also joke about it as a way to cope.
One thing that contributes significantly to the decline in healthcare is the interference that doctors and nurses experience from the patient’s insurance company. The Journal of Advanced Practice Nursing explains that insurance providers sometimes deny medical care based on cost and force hospital workers to spend more time documenting than actually caring for patients.
Medical practitioners sometimes have to cater to strict provider rules and receive low scores if they don't meet all the absurd criteria. This kind of structure might benefit patients sometimes, but it can also cause problems with care and treatment.
 My place of work uses a patient's blood to make eyedrops for them. Pretty cool that your body can help make medication that can help keep your eyesight.
 CPR is done on people who are technically d**d. Because something catastrophic within their body has occurred. Which is why it’s so aggressive.
Also, the success rate of CPR on a healthy, YOUNG adult is 9-16%.
A lot of people assume that their healthy elderly loved ones are going to be just fine with no deficits after having to go through this intervention. The after effects are much starker than what the media portrays. The reality is that after going through an event that required CPR, your quality of life will drastically change. And for a lot of people, it’s a change that is not worth it. They would have rather died being independent til the end, even though it was a shorter life, than have some months/years added with lots of new, incapacitating health and function issues that rob them of their independence.
CPR in patients over 80 yields poor survival rates, with only 15–21.5% surviving to discharge after in-hospital cardiac arrest and as few as 2.8–8% after out-of-hospital arrest, with 1-year survival approaching zero for the latter group. Among the small minority who do survive to discharge, neurological recovery is often reasonable, but long-term quality of life is substantially diminished, with high rates of rehospitalization, depression, and functional decline.
 When giving IM injections it’s not uncommon to hit bone, especially on older people.
They don’t feel it, but you do! Trick is not to panic and just ease back a little.

I recently had to take my first child for her 6-8 week injections. Our doctor suggested we wait until 7-8 weeks, to make sure she had thicker legs so they were less likely to hit bone.
It might seem crazy that so many extreme things done in hospitals have been kept under wraps, but the Editors of Prevention mention that it could be because your doctor is lying to you. They explain that a study on 2,000 physicians found that they tend to tell white lies very often.
These untruths could involve the quality of care, the patient’s diagnosis, and other information, either because they fear malpractice suits or to keep the individual from panicking. This is why patients need to be cautious about putting all their trust in their medical provider, and instead also trust their own instincts when it comes to their care and treatment.
 I graduated nursing school at the tail end of covid so my hands on experience with nursing skills was limited. I had a residency in the ICU, where everyone has a central or arterial line that's placed by a special team, and needed to learn basic IV placement. My educator suggested I pick one of the intubated and sedated patients and stick them. When I looked horrified she changed her answer to "...you know, if they need it." None of them would have needed it.
I did not stay in the ICU.
 Doctors no longer consider pain, even when severe, is not a medical concern. They will make you just suffer with no help or comfort.
This is the type of practice that we will look back on in 50 years and say “Oh my god I can’t believe we used to do that to people!”
Depends who you are. You live in the right tax bracket and you can get whatever medical care you want even for the most minor pain relief.
 The “OB handshake”. Sometimes when a c-section is called after the patient has been pushing for a while, the surgeon needs pressure pushed up on the babies head to safely deliver them since they have been wedged/stuck so far down. The nurse puts on a sterile glove during surgery, goes under the drape and has to insert their hand to gently put pressure up on the babies head. Sometimes you and the doctor feel each others hands and then you realize you’re basically shaking hands through and entire human. Thankfully someone very smart invented a product called The Fetal Pillow, to more safely achieve the same result but most facilities don’t have this.
Hospitals and treatment facilities are still places where people come to get better and learn how to care for their health. That’s why doctors also need to meet their patients' emotional needs, not just improve their physical health. Medical Economics explains that you can do this by adopting a people-first approach and helping folks feel comfortable.
Medical professionals should smile and take a few moments to get to know their patients, rather than just reviewing their intake form. It can also help to treat every individual consistently, whether the problem is minor or severe, because folks may feel less anxious about the process.
 The over use of radiation to “fish” and see what is wrong with someone. Just radiating and guessing a prognosis.

It is frequently done to make sure something more serious is not missed. Modern digital x-rays use a fraction of the dose that the old film type used. CT and MR scans can look for things that really could never be seen by physical examination and which to be a precursor to a major problem of which the current symptom is only a small part. I'm very glad they scanned me for metastases when my tumour markers went back up again 18 months after chemo.
 The amount of technicians with only a week of on the job training who are making complex medical decisions for you because the doctor can’t be bothered to review your file.
Postmortem care and discretely moving the body to a back elevator. The morgue at the facility I was training at was located in the basement. Being in an elevator with a d**d body, and hitting the "down" button is a uniquely creepy feeling.
Being in the medical field isn’t easy and requires a lot of hard work from doctors, nurses, and staff. It’s also important to keep learning and brushing up on new topics so there is always room for unique and powerful treatments.
Professionals explain that any trainee in the field should listen carefully to their patient’s experience and integrate that with their own expertise to provide the best care. This kind of competent work can improve their standing in the medical field and build a strong patient base.
 Blunt dissection. If people saw their tissues being torn apart instead of being delicately incised they would be horrified.
Electroconvulsive therapy is still used in psychiatry. Most people assume it's a barbaric and outdated practice, and the only people using it still must be sa***ts. It's actually still one of the most effective tools for severe depression if meds arent helping.
Cracking a chest wall as a last ditch effort to restart a heart after a traumatic arrest. .

There’s so much about what happens behind the scenes at medical practices that we might never truly know about. These secrets might already be quite shocking to come to terms with, and may even color your view of the folks working in the field.
Regardless of that, it’s important to understand that every profession harbors something dark, and that we might have to just take the good with the bad. Do you know any things about hospitals that we might find shocking? If so, do expose them in the comments below.
 The amount of lost tampons we have to fish out.
One of many reasons those things and diva cups scare me. If you use them then great! But I'm too worried they'll get stuck.
 Apparently they have residents do pelvic exams on women under anesthesia just for the residents to practice. The woman might have been under anesthesia for a totally non pelvic surgery like broken arm, gallbladder, ect.
Why do you call it 'pelvic exam'? It has almost nothing to do with the pelvis and all to do with the v****a. Feels so awkward.
In long term care we talk you into putting mom/dad/grandpa/grandma on a DNR… a lot of families get so offended at the thought; but they don’t realize the other option is crushing their ribs.
 They literally run your blood through a cooling system to lower your body temperature during certain procedures.
This lowers metabolism, and gives the surgeons a longer window to safely finish the procedure.
The patient's blood runs cold, and then gently warmer to bring them back.
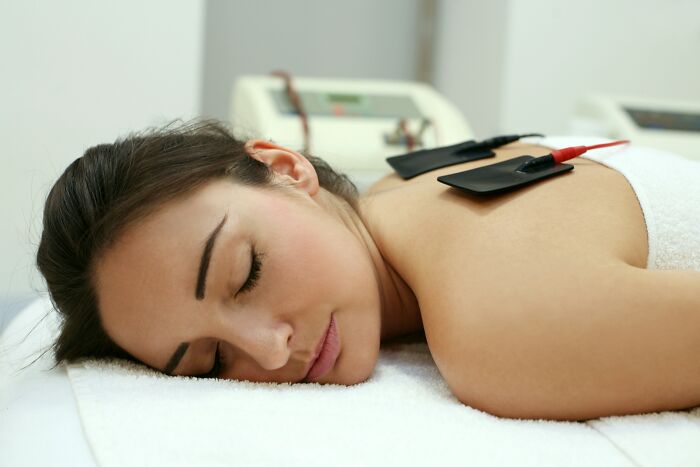 Electroconvulsive Therapy. It’s a lot safer now but it’s still inducing a seizure multiple times a week for about a month.
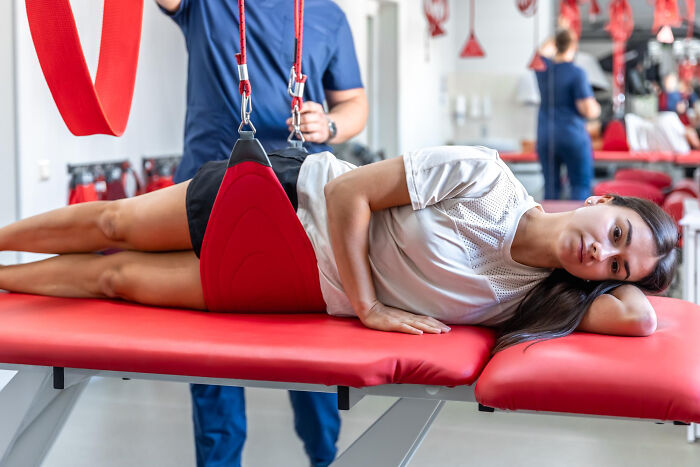 I work in trauma ORs and just like… the way you have to move spine patients for posterior approach procedures looks insane. There are protocols to do it as safely as possible but every so often I’m still like, ok so we just toss em, got it. (We do NOT just toss them, it’s a controlled roll but looks wild).
To those commenting on the CPR on a 90 year old - I read Being Mortal by Atul Gawande and it’s about how we treat the aging and dying in the medical world but also just in the world in general and it is all so sad and harrowing. It’s a phenomenal book and there are some high points but wow it gives you a lot to think about.
 They're still using leeches for certain things.
Don't ask how I know. Last week was rough...
The way you can be holding a fat flap or handling some guys insides one minute and then casually eating lunch during your break immediately afterwards.
 Morbid humor as a way of coping. Circling the drain. Horizontal transfer. Celestial discharge. It all sounds so gross, but it's just how some people handle stress.
 There are unfortunately too many medical reasons to stick your finger in an elderly gentleman’s b**t…
Advice for newbie medics: always double glove in the above scenario.
If they are the same as condoms, double gloving will cause them to tear more easily because of the friction, so less safe.
Normal O2 before COVID for a healthy patient used to be 95-96+. Now no one gets alarmed unless the patient is under 90%+. Due to the fact that it seems most of us lost a little bit of lung function due to COVID.

The way nurses (not all- but most) try to manage type one diabetes is laughable.
 We can make medicine out of our blood platelets and plasma. And p**p.
Dressing foot/leg wounds is enough for me to never want to eat again.
Oh thee of faint heart. I guess you've never had to de-maggott a maggotty rabbit!!
How clean/sterile the Operating Theatre is trusted to people like or not like me. I am extremely thorough and methodical taking about 2 hrs but some of my co workers would take 30 mins max.
Doing pelvic exams on unconscious women during unrelated medical procedures without needing consent.
In the UK ,according to the General Medical Council, doctors must never perform an intimate examination on an unconscious or anaesthetised patient solely for educational or training purposes unless explicit consent was given in writing or logged in your records beforehand.
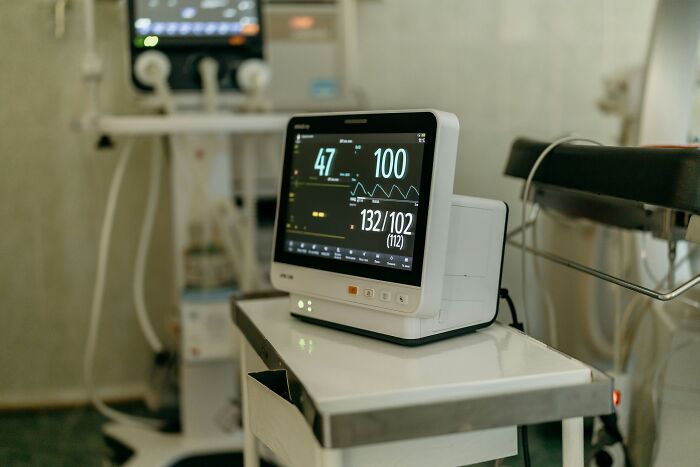 Monitoring cardiac screens for the entire hospital. Especially when they place monitors on a DNR patient just to charge insurance!
Surely the monitor on dying patients isn't just to make money. Doctors and nurses will still need to monitor them leading up to d***h because they need to make sure their body isn't too stressed and give medication etc to make them more comfortable.
Doctors lying to patients.
This needs far more context. Personally, I'd want any doctor to be honest with me. Brutally honest, if that's what's needed for me to properly understand my situation. But, some people can't handle the truth.
 Several hospitals have been sued for neglecting to save organ donors.
Writing notes on paper, violating GDPR by having patient notes on whiteboards or lying around on Wards. It's not the 1950s any more, this needs to stop.
I'd be very interested to know where this was, given the use of GDPR. When I was on a NHS cardiology ward two years ago it was nothing like this. Every interaction with the medical staff, even just checking blood pressure, was recorded on computer, which they wheeled around the ward. And, before anything else was done they would check your little plastic bracelet and ask a couple of questions to confirm that they were looking at the correct records.
Emergency c section-surgeon literally tore open that women’s uterus with his hands (after initial incisions)
Edited to add: manual revision of uterus after delivery to treat hemorrhage…f*****g barbaric.
If you d*e in a nursing home and no one is your POA and you have no family and no funeral arrangements and no one clocks this before you d*e they have to wheel your bed into whatever room has the lowest temperature while someone runs to probate court to petition for authority to have your body cremated.
Bone marrow donation. My daughter got ~80 needle sticks to extract a liter of bone marrow. We heard from providers who were watching that it was the worst thing they had ever seen. A huge amount of force to twist and drill into the bone. She's still in pain 2.5 years later...
When I worked in the emergency department, sometimes when EMS called in a cardiac arrest with a prolonged downtime in the field, the nurses would put the body bag on the stretcher before the patient arrived.
When you're d**d, you're d**d. EMS are able to tell. The bag is not sealed until a physician checks anyway.
Even CPR on someone who has had 20 hospital admissions this year and is in terrible health in their 70s. I just had a 20 minute code for a guy who I had on my floor every other month all year. Dude never should have been a full code.
Some of the conversations that occur in an operating theatre during surgery.

My doc thought I was out cold during my procedure and had an adorable conversation with her nurse regarding her new puppy. I freaked them both out when I piped up with "what's the puppy's name?"
 Australia I am not sure how it works in other countries
Palliative care in hospital. Medication, food, water ceased. Just mo****ne. You have 5 days max.
It's basically a d***h sentence.
My mother died last week. She refused food and water, all she was given was Xanax and (apparently censored, so let's see if I can get past it) m*rph*n*. Her body was saying it was time to go. She had had dementia for several years, and didn't remember anything--even who I was. IT WAS HER TIME TO GO. WHAT'S SO BAD ABOUT THAT??
 Hospitals tolerating 007s.
That's a doctor widely known to be so bad he has "a license to k**l.".
Eating minutes after doing cpr like it's nothing.
So many foreign body removals. Barely noticing when there is body fluid on your clothes.
Calling a patient who is deceased - "Expired" first time I read that I was in shock. Still makes me feel icky.
Deciding who to bother helping in a mass casualty event, you are going to be leaving people to d*e.
Nurses skipping pain relief for children getting injections to save on time.
What kind of injection are they talking about,though? I took my daughter for all her childhood vaccinations, and there was never any need for pain relief.
The cure to compartment syndrome.
When you know why, it makes sense, but if you've ever seen it, it looks barbaric.
Compartment syndrome can happen when a part of the body is crushed for so long that toxins build up in the tissues. If these toxins are suddenly released they can flood the system causing d***h. Sometimes in an acute situation amputation may be the only way to save the patient. Think traumatic injury caused by being buried in rubble or being in a train crash.
As a firefighter paramedic, I’ve gone to PNB calls where a family member witnessed the d***h of an individual. That individual then calls the whole family to start dividing their positions before they are pronounced d**d.
I pretty sure hospital staff can’t do any thing it has to be signed ahead of time you might even need two signatures from two different doctors is a pretty tight legal thing so just don’t think for asking that you’re gonna get it from anyone.
Donation after circulatory d***h (DCD) vs a pt being declared brain d**d.
Giving a high mo****ne dose when someone is dying.
Mo****ne in a high dose will shut down a person's organs, so you do the maths.
So,it's speeds up the inevitable but the patient is completely unaware. And the problem is?
So as I said, I went to my doctor and asked for him to sign a form per DNR and he said no he didn’t give me a reason, but from what I know about DNR‘s, I looked into it. You need to go to your doctor to get a form they are there’s numbers on these forms which means something so they have to be ordered ahead of time then you bring it to your doctor and he will sign it but in my case he didn’t I’ll never like this doctor. I can’t stand them from my doctor for 40 years and he is a buffoon.
I think you are supposed to get a DNR witnessed by a lawyer or at least a Notary Public, not a doctor.
Never curing any disease and pushing unneeded d***s on people.
Making a big deal about 2 measles deaths and accepting 626,140 cancer deaths per year as business as usual.
But if you don't make a big deal about measles, those 2 turn into 626,140 measles deaths per year.

One thing that really annoys me as a Physiotherapist is incomplete or inaccurate medical notes, and it is often GP's that are the problem. Not having a patient's complete history sometimes makes it very difficult to draw up a treatment plan that is appropriate. Another issue is when I try to prescribe medication and the patient tells me, and often shows me that their medication is different to what are on their records so I then have to try to contact their GP to find out what they have been prescribed so I know what medications I can and cannot prescribe.
FFS do some people go through life expecting nothing but flowers and puppies and sunshine?

One thing that really annoys me as a Physiotherapist is incomplete or inaccurate medical notes, and it is often GP's that are the problem. Not having a patient's complete history sometimes makes it very difficult to draw up a treatment plan that is appropriate. Another issue is when I try to prescribe medication and the patient tells me, and often shows me that their medication is different to what are on their records so I then have to try to contact their GP to find out what they have been prescribed so I know what medications I can and cannot prescribe.
FFS do some people go through life expecting nothing but flowers and puppies and sunshine?




































 No fees, cancel anytime












